The best hospital beds for home are fully electric models with a low-height range, independently adjustable head and knee sections, a compatible pressure-relieving mattress, locking casters, and rails that match the user’s mobility needs rather than simply covering the entire side.
For most home caregivers, a full-electric bed is the best starting point because the user or caregiver can adjust the backrest, knee section, and overall height without manually cranking the frame. Bariatric users, people at high fall risk, and homes with tight doorways may need different priorities. The right choice depends on the interaction between the frame, mattress, rails, room, and caregiver—not the frame’s feature list alone.
As an Amazon Associate we earn from qualifying purchases at no extra cost to you.




Our Top Picks
 HaiyoHBED 5 Pro Function 600LBS Full Electric Hospitalmodel-C83.7 x 38.6 x 17.6 inches240 PoundsCheck on Amazon
 Fuzren Premium Full Electric Hospital Bed for HomeL-5 Function Upgrade86.29 x 39.79 x 17.73 Inches242 PoundsCheck on Amazon
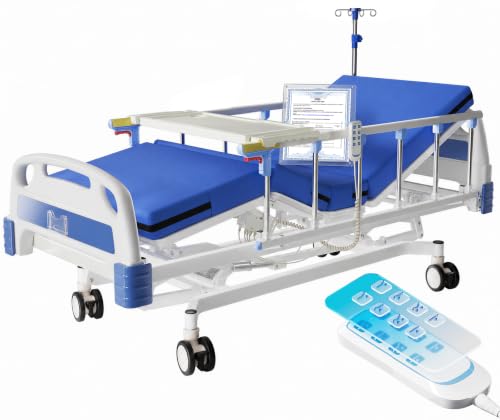 HaiyoHBED 4 Function 600LBS Full Electric Hospital Bedmodel-A83.7 x 38.6 x 17.6 inches240 poundsCheck on Amazon
 HaiyoHBED 5 Function 600LBS Full Electric Hospital Bedmodel-B83.7 x 38.6 x 17.6 inches240 poundsCheck on Amazon
Top 3 picks at a glance
Quick comparison: which home hospital bed fits?
| Home situation | Best bed class | Useful specifications | Why it fits |
|---|---|---|---|
| Routine recovery or long-term care | Full-electric standard bed | 36-inch width, 450–600 lb capacity, 15–23 inch height range | Good balance of positioning, caregiver access, and room fit |
| User can help with transfers but needs repositioning support | Electric bed with half-length or split rails | Independent head and knee adjustment, removable rails | Provides handholds without making every exit feel enclosed |
| High fall risk or frequent overnight care | Low-height electric bed | Minimum height around 7–10 inches, locking casters, compatible safety rails | Reduces the distance to the floor if a fall occurs and improves caregiver access |
| User weighs close to the standard limit or needs more turning space | Bariatric full-electric bed | 42–48 inch width, 700–1,000 lb capacity or higher | Provides additional structural margin and usable surface width |
| Small bedroom, narrow hallway, or frequent room changes | Compact or split-frame bed | Tool-free assembly, removable headboard, 5-inch casters or larger | Easier to move through doorways and reconfigure indoors |
Adjustable positions: prioritize useful movement
A good home bed should offer three separate functions: head elevation, knee or foot elevation, and overall height adjustment. The first two improve comfort and can help with eating, reading, breathing comfort, and reducing sliding toward the foot of the bed. Height adjustment is primarily a caregiver feature: it can bring the mattress to a safer working level for changing linens, bathing, dressing, and transfers.
Look for a handset that controls the head and knee sections independently. Some beds add a “chair” or “contour” position, which raises the back and knees together. This can be convenient, but it should not replace independent controls. A handset with large, clearly separated buttons is easier to operate at night or with limited dexterity.
Ask how the bed behaves after a power interruption. Most electric hospital beds can remain in their current position when unplugged, but they generally cannot be adjusted without power unless they include a battery backup or manual emergency release. Keep the power cord away from walkways, and do not use an extension cord unless the manufacturer specifically permits it.
Mattress compatibility matters more than the frame brand
Hospital-bed mattresses are not interchangeable with ordinary twin mattresses. A standard home hospital bed commonly takes a mattress about 36 inches wide by 80 inches long, but dimensions, corner radius, thickness, and attachment features vary. Bariatric beds may require a 42- or 48-inch mattress, while some specialty frames use different lengths.
Before buying, confirm all four measurements:
- Usable deck width and length, not just the outside frame dimensions.
- Maximum mattress thickness allowed with the selected rails.
- Whether the deck bends enough for the mattress’s minimum bend radius.
- Whether the mattress has straps, a contoured underside, or other retention features.
Mattress thickness changes the effective rail height. For example, if a rail rises 11 inches above the deck and the mattress is 8 inches thick, only about 3 inches of rail remain above the mattress. That may be insufficient for the intended safety purpose. Conversely, a very thin mattress can leave excessive gaps or make the surface uncomfortable.
For users who spend most of the day in bed, consider a pressure-redistributing foam, alternating-pressure, or low-air-loss mattress only when it is confirmed to work with the frame and rail system. A mattress that is too soft, too tall, or too wide can affect transfers and increase entrapment risk.
Weight capacity: calculate a margin, not a match
Manufacturers may list patient weight capacity, safe working load, or both. These terms are not always identical. Safe working load can include the user, mattress, bedding, accessories, and any equipment attached to the bed.
Use this calculation before choosing a frame:
Required capacity = user weight + mattress weight + accessories + safety margin.
Example: a 275-pound user uses a 35-pound therapeutic mattress, 10 pounds of bedding, and 15 pounds of attached accessories. The loaded bed weight is 335 pounds. Adding a 20% planning margin gives 402 pounds, so a 450-pound rated bed may be suitable on paper. If the user is close to 400 pounds, however, a 450-pound frame leaves little practical margin; a 600-pound model is the more sensible class.
Do not assume a bariatric frame is automatically better for every user. It may be wider, heavier, harder to steer, and more difficult to fit through a bedroom door. Choose the smallest bed that provides adequate width and capacity with a meaningful margin.
Rails: choose access and protection separately
Full-length rails can help with rolling, provide a handhold, and prevent some accidental exits, but they can also obstruct transfers and create a temptation to climb over them. Half-length rails or split rails usually offer a better compromise for users who need support getting in and out of bed.
Check whether the rails are:
- Designed specifically for the frame, rather than adapted from another model.
- Easy for the caregiver to lower from outside the bed.
- Compatible with the chosen mattress thickness.
- Free of openings that could trap the head, neck, chest, or limbs.
- Strong enough to serve as a positioning aid, if the manufacturer allows that use.
A rail is not a substitute for supervision or a fall-prevention plan. If the user is confused, repeatedly tries to climb over the rail, or becomes trapped against it, contact the prescribing clinician or occupational therapist for a safer arrangement.
Casters and brakes determine whether care feels manageable
Four locking casters are the minimum to look for, but caster quality affects everyday safety. Larger casters—around 5 inches or more—usually roll over thresholds and thick flooring more easily than small casters. Dual-wheel casters can improve stability, while a central brake system lets the caregiver lock all wheels from one location.
Check the route from the delivery point to the room before ordering. Measure the narrowest doorway, account for the frame’s diagonal turning clearance, and identify thresholds, rugs, elevator doors, and tight corners. A bed that fits through a doorway may still be impossible to turn into position.
Once installed, press the bed from several directions with the brakes engaged. The casters should not roll or swivel freely. Recheck the brakes after moving the bed; locking mechanisms can be left partially engaged if the pedal is not fully pressed.
Setup requirements for home caregivers
Ask whether the bed arrives as a split frame or a single assembled unit. Split-frame designs are generally easier to carry upstairs and through narrow halls, but they require correct joining of the two sections and connection of the motor cables. Keep the manual and handset with the bed, not in a separate storage box.
A practical setup sequence is:
- Measure the route and clear a working area around the final location.
- Assemble the frame exactly as directed; do not substitute bolts or hardware.
- Install the mattress retainer, rails, and head- or footboard before placing the mattress.
- Route cables beneath the frame or through the manufacturer’s cable guides, away from casters and pinch points.
- Test every handset function with the bed empty.
- Test the lowest and highest positions, rail movement, caster brakes, and emergency lowering feature.
- Place the mattress and repeat the rail and position checks under normal load.
Allow a clear transfer side, commonly at least 30 inches where the room permits. Leave enough clearance at the foot for caregivers to change linens and enough space around the head for cable access. Avoid placing the bed where a raised back section can strike a wall, window, radiator, or medical equipment.
Best-value feature priorities
General market pricing is often about $400–$800 for a basic manual or semi-electric bed, $700–$1,500 for a standard full-electric setup, and $1,500–$3,500 or more for bariatric, low-height, or advanced therapeutic systems. The mattress, rails, delivery, assembly, and rental or service arrangements can add substantially to the total.
If the budget is limited, spend first on a reliable full-electric frame, a correctly compatible mattress, secure brakes, and the rail configuration the user actually needs. A remote-control light, decorative headboard, or extra accessory is less important than a low minimum height, smooth adjustment, and a setup that caregivers can operate without lifting the user manually.
Frequently asked questions
Can a home hospital bed be adjusted during a power outage?
Usually not, unless the bed includes a battery backup or manual emergency release. Most electric hospital beds can remain in their current position when unplugged, but their adjustments generally will not work without power. Before buying, ask how the bed behaves after an interruption and whether either backup feature is included. Keep the power cord away from walkways.
Can I use an ordinary twin mattress on a home hospital bed?
No, ordinary twin mattresses are not automatically interchangeable with hospital beds. Confirm the usable deck width and length, maximum mattress thickness, minimum bend radius, and any required straps or retention features. Standard beds commonly use mattresses about 36 inches wide by 80 inches long, but dimensions and attachment features vary by frame.
How can I tell whether a mattress is too thick for the bed rails?
Compare the mattress thickness with the rail height above the deck. For example, an 11-inch rail with an 8-inch mattress leaves only about 3 inches of rail above the mattress, which may be insufficient for the intended safety purpose. Also confirm that the mattress is compatible with the frame and does not create excessive gaps or affect transfers.
What should I check before moving the bed into the bedroom?
Measure the narrowest doorway and account for diagonal turning clearance before ordering. Also check thresholds, rugs, elevator doors, and tight corners along the route from delivery to the room. A bed may fit through a doorway yet still be impossible to turn into position. Split-frame designs can be easier to carry through narrow halls, but they require correct assembly.
How should I decide whether the bed needs full-length or half-length rails?
Choose rails according to the user’s mobility and need for access, rather than automatically selecting full-length rails. Half-length or split rails can provide handholds while making bed entry and exit easier. Full-length rails may help with rolling and some accidental exits, but they can obstruct transfers and may encourage a user to climb over them.
Final buying checklist
- Does the bed’s patient capacity leave a practical margin after adding the mattress and accessories?
- Do the frame dimensions match the intended mattress exactly?
- Will the selected mattress leave enough rail above its surface?
- Are head, knee, and overall height controls independent?
- Can caregivers lower the bed for transfers and raise it for personal care?
- Do the casters fit the flooring and lock securely?
- Will the bed pass through every doorway and turn in the destination room?
- Are replacement rails, handset controls, motors, and mattresses available?
- Has a clinician or occupational therapist advised on rails, fall risk, or positioning?
For most households, the strongest all-around choice is a standard full-electric bed with a low-height range, a 450–600-pound capacity, a compatible pressure-redistributing mattress, split or half-length rails, and large locking casters. Move to a bariatric or specialty low-height model when the user’s weight, fall risk, room layout, or care routine makes those features necessary.